Diabetic Foot Ulcers and Infections
Worldwide, diabetes affects over 500 billion individuals, a number that is growing rapidly due to the aging population, increasing incidence of obesity, current sedentary lifestyles, and poor eating habits.1 Consequences of diabetes include shorter lifespans and reduced quality of life, in part due to the occurrence of numerous additional health conditions including impaired vision, acute myocardial infarction, renal failure, stroke, and peripheral neuropathy and peripheral arterial diseases, such as diabetic sensory–motor polyneuropathy.1 In patients with poorly managed diabetes (about one-third), the latter, in combination with poor circulation and immune system impairment, leads to diabetic foot ulcers (DFUs).2,3
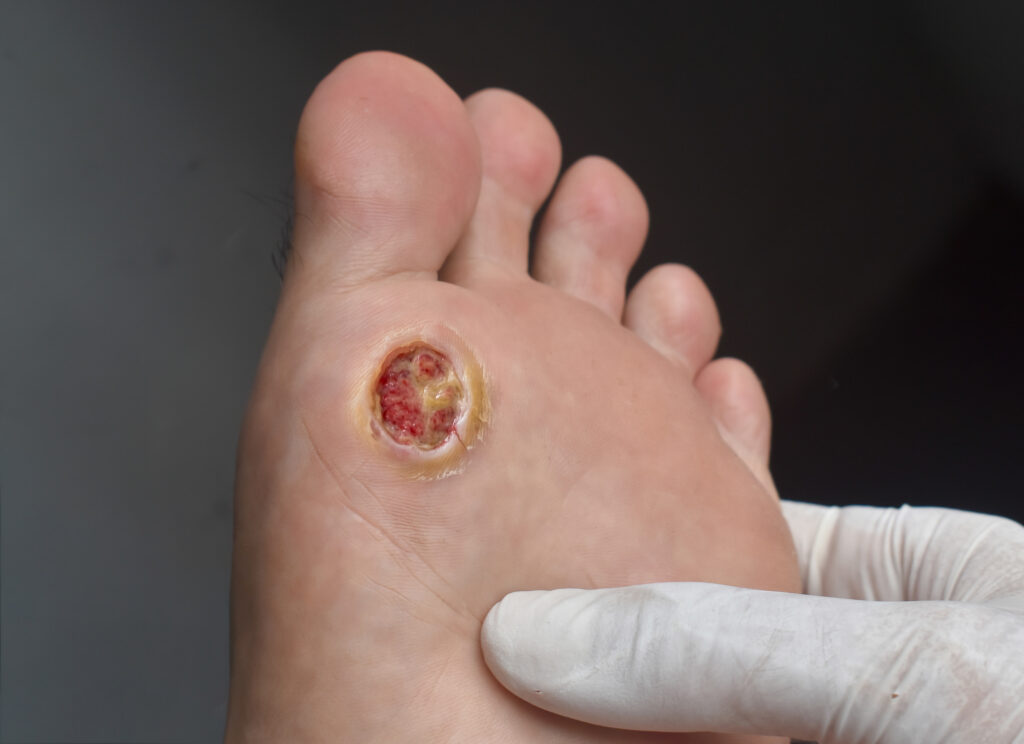
DFUs often form in weight-bearing and high-pressure areas because patients lose sensation in their extremities and thus do not notice injuries. Poor immune responses and circulation prevent effective wound healing, leading to increased infection risk.3 Approximately half of DFUs become infected.
Diabetic foot infections (DFIs) can occur in soft tissue or bone and often lead to hospitalizations, the need for surgical intervention, and amputations.2-5 The severity of the infection typically depends on the size and depth of the ulcers, with those that are larger and deeper having greater risk for additional complications including osteomyelitis and sepsis.
Many infections are caused by multiple bacterial species (polymicrobial), with increasing percentages being resistant to one or more common antibiotics, including clindamycin, co-trimoxazole, amoxycillin, ampicillin, ciprofloxacin, cefepime, vancomycin, and linezolid. In 2025, approximately 18.5 million people annually were estimated to be affected by DFIs.3 Furthermore, about half of those infections involved multidrug resistant (MDR) pathogens.
Numerous Problematic Bacteria
Isolates collected from DFIs often comprise both Gram-negative and Gram-positive bacteria, including Pseudomonas aeruginosa, Escherichia coli, Enterobacter, Enterococcus, Klebsiella pneumoniae, Proteus spp., Staphylococcus aureus, Streptococcus, Veillonella, and Bacteroides species.1–4 High levels of resistance have been observed by many of these bacteria against a wide range of older, broadly used antibiotics, including ampicillin, ciprofloxacin, levofloxacin, trimethoprim–sulfamethoxazole, and cefuroxime.
Several factors influence the specific compositions ranging from patient-specific (e.g., properties of the ulcer, prior antibiotic use, immune health, other comorbidities, length of hospital stay) to broad (e.g., hospital practices, geographic location).
In a meta-analysis of DFI reports covering a 10-year period (2014-2024), S. aureus was the most prevalent isolate, with nearly a quarter being MDR strains including MSRA (methicillin-resistant S. aureus). Pseudomonas and Enterobacter species were also common.3 In chronic polymicrobial DFIs, Staphylococcus spp. and Streptococcus spp. typically predominate, with Gram-negative bacteria present as co-pathogens.2 More severe DFIs have been associated with Pseudomonas spp. and Enterobacter spp., particularly in patients with compromised immunity and poor wound healing.3
Growing Issues with Polymicrobial Infections, MDR, and Biofilms
The presence of MDR pathogens in DFIs has been increasingly steadily. One study of approximately 150 patients with infected DFUs found that about 95% of the Gram-negative bacteria and 60–87% of the Gram-positive bacteria were resistant to 9–11 commonly used antibiotics.2 High levels of MDR have been reported in isolates from DFIs collected during studies in diverse locations around the world. Leading MDR pathogens include Acinetobacter spp., S. aureus, coagulase-negative staphylococci (CoNS), Streptococcus spp., and Enterococcus spp.3
Furthermore, evidence has been collected suggesting that the mono-resistant bacteria have a high risk of becoming multi-resistant.3 Those species at high risk for developing MDR (through predictable progression) include S. aureus, CoNS, Pseudomonas, and E. coli. Others that can be difficult to anticipate (“silent MDR threats”) include Corynebacterium spp., Enterococcus spp., and Acinetobacter spp.
Bacteria that form biofilms create further challenges for treatment of DFIs. In addition to acting as a protective barrier, these matrices generated by some bacteria support symbiotic growth of different bacterial species and provide an environment conducive to the development of antibiotic resistance. Diabetic foot ulcers infected by bacteria that generate biofilms experience reduced wound healing and tend to be chronic. As a result, they require extended antibiotic treatment and the use of high antibiotic concentrations, both of which often lead to MDR development.2
Many Risk Factors for Infection by Resistant Strains
Development of MDR in bacterial species present in DFIs can be attributed to a number of different factors.3,6–8 In addition to the presence of biofilms, direct causes of MDR development can include ulcers that remain for long periods, recurrent ulceration, the number of hospitalizations and lengths of stay, and repeated and extended antibiotic use. Poor management of diabetes resulting in uncontrolled blood sugar and ongoing peripheral vascular disease, hypertension, peripheral neuropathy, and chronic kidney disease (CKD) all indirectly contribute to an environment that encourages bacterial colonization and growth and the selection of resistant strains. Smoking, meanwhile, “exacerbates all the pathological mechanisms underlying DFIs” and makes wound healing difficult, leading to prolonged infections and greater opportunity for growth of many bacterial species and development of resistance.3
Important Geographical Differences
Several reports exist in the literature describing the analysis of isolates collected from patients with diabetic foot infections. Studies have been conducted in hospitals in Peru, Brazil, Malaysia, the West Bank, China, Germany, and many other regions and countries. The composition of bacterial species varies greatly from one study to the next.
• Of 181 patients with DFIs in a tertiary-care hospital in Peru, 32 bacterial species were identified, 63% of which were Gram-negative bacteria.1 The most common pathogens were S. aureus, E. coli, P. aeruginosa, P. vulgaris, and M. morganii. They exhibited resistance to ampicillin, ciprofloxacin, levofloxacin, trimethoprim–sulfamethoxazole, and cefuroxime, with E. coli the most resistant.
• Analysis of cultures taken from DFUs in 459 patients at a Brazilian hospital provided evidence of 337 DFIs.4 Gram-negative bacteria accounted for 55.2%, with Enterobacterales and non-fermenters most prevalent and with significant resistance to extended-spectrum beta-lactams (ESBL) and quinolones.
• Among 118 patients in the Vascular Surgery Department at a hospital in the West Bank, Palestine, identified as having DFIs, Gram-negative bacteria were more prevalent (58.8%), and the most common pathogens were determined to be S. aureus, E. coli, and P. aeruginosa.5 Resistance against ESBLs, carbapenems, and methicillin was observed, with a high prevalence of MDR strains.
• The bacterial profile of infections in 153 DFU patients in Malaysia found Gram-positive bacteria to predominate (62%), with S. aureus and CoNS present with the highest frequency.2 More than 60% of the Gram-positive and 95% of the Gram-negative species exhibited MDR.
• In isolates obtained from Chinese DFU patients, Gram-positive bacteria exhibited resistance to numerous antibiotic classes, including beta-lactams, aminoglycosides, macrolides, fluoroquinolones, and tetracyclines, while Gram-negative bacteria were resistant to cephalosporins.
• In other studies, samples from German DFIs were found to contain few MDR bacteria, while those from patients in Southern China has a 40% prevalence of MDR bacteria, and the majority of bacteria in isolates from DFIs in Bangladeshi patients were MDR.2
The study conducted in Malaysia found most bacteria to be susceptible to aminoglycosides and the beta-lactam antibiotic imipenem (in the Reserve (R) category of the World Health Organization AWaRe classification and not widely used) and resistant to clindamycin, amoxicillin, and ampicillin.2 Only ciprofloxacin was effective against all bacteria. Except for S. pyogenes and S. aureus, the isolated bacterial species were highly resistant to linezolid and vancomycin. Moderate to high resistance was also observed against the first-generation cephalosporin cefazolin. Fourth-generation cefepime was more effective against Gram-negative bacteria.
These results clearly show how the bacterial composition and resistance patterns in DFIs vary in different geographic locations.
Higher Resistance Correlates to Higher Risk for Amputation and Death
DFIs populated with bacteria resistant to antibiotics pose significant treatment challenges. Extended infections can lead to worsening of ulcerations in terms of size and depth. They also require longer hospital stays and antibiotic treatment regimens, both of which can contribute to further colonization of MDR bacteria. As a result, DFIs comprising MDR bacteria have a much higher risk of resulting in amputation and mortality.1,2,5
Active DFU Management Is Essential
The potential for infections of diabetic foot ulcers to be complicated by resistant bacterial strains creates the need for early and proactive DFU treatment to prevent development of chronic ulcers and MDR infections.1–5 That starts with implementing an appropriate treatment regimen and lifestyle changes for diabetes patients to ameliorate the many complicating conditions that contribute to the development of DFUs, DFIs, and antibiotic resistance. It also includes active monitoring for the presence of DFUs so they can be treated as soon as they appear and before they have the opportunity to become infected.
If infection does occur, treatment with oral antibiotics should be initiated while an infection is mild to moderate. Severe, deep, or systemic infections typically require treatment with broad-spectrum intravenous antibiotics. However, it is important to note that the high variability in the bacterial composition of DFIs from one location to another and one patient to another requires tailored treatment programs established following effective analysis of isolates. Collection of deep tissue samples using aseptic practices is essential to ensure isolation of bacteria present within the DFU/DFI (not just on the skin). Identification of specific bacterial species and determination of their level of resistance to various antibiotics should guide treatment decisions. Use of targeted treatment protocols has been shown to enable improved clinical outcomes.
Indeed, the expanding body of evidence surrounding the increasing presence of MDR bacterial species in DFIs highlights how essential the careful use of antibiotics is during treatment of these challenging infections. Effective antimicrobial stewardship must be a key component of any treatment strategy, which must consider both the choice of antibiotics and timing of their administration.